
Related service at Sleep and Lung Care: Respiratory physician consultation
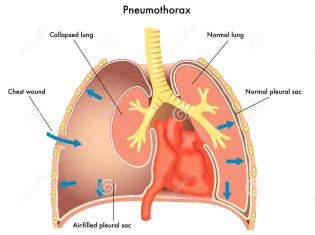
A collapsed lung, known medically as a pneumothorax, happens when air leaks into the narrow space between the lung and the chest wall. The trapped air presses on the lung so it cannot expand properly, causing sudden one-sided chest pain and shortness of breath. A small pneumothorax often heals by itself within a few weeks, a larger one is usually drained in hospital, and a tension pneumothorax, where pressure builds quickly, is a medical emergency.
Key points
- It can strike without warning in healthy people, most often tall, slim young men and smokers, or complicate lung disease or a chest injury.
- Sudden sharp pain on one side of the chest and breathlessness are the main symptoms. Call Triple Zero (000) if breathing is very difficult, lips turn blue, or the person collapses.
- A chest X-ray confirms it. Treatment ranges from careful watching to a needle, a chest drain or keyhole surgery.
- About one in three people have another one, so stopping smoking, the flying and diving rules and specialist follow-up all matter.
What is a pneumothorax (collapsed lung)?
Each lung is wrapped in two thin, slippery layers of tissue called the pleura, with no air between them, so the lung slides smoothly against the chest wall as you breathe. A pneumothorax occurs when air gets into this pleural space, through a leak on the surface of the lung or a wound in the chest wall, and the lung on that side collapses partly or, less often, completely.
“Collapsed lung” is also sometimes used for atelectasis, where part of a lung deflates because an airway is blocked, for example by mucus after surgery. That is a different problem; this article is about pneumothorax.
What causes a collapsed lung, and who gets it?
Primary spontaneous pneumothorax happens out of the blue in people with no known lung disease, most often between the late teens and mid-thirties, in men more than women, and in people who are tall and slim. The usual cause is a tiny air blister on the surface of the lung, called a bleb, that bursts. Smoking is the biggest avoidable risk factor: smokers are many times more likely to have a pneumothorax than non-smokers, and the risk rises with the amount smoked. Case reports also link vaping with pneumothorax, although the evidence is still emerging.
Secondary spontaneous pneumothorax is a complication of an existing lung condition, most often chronic obstructive pulmonary disease (COPD, which includes emphysema). Severe asthma, cystic fibrosis, pneumonia, tuberculosis, lung scarring (pulmonary fibrosis), lung cancer and some inherited connective tissue conditions such as Marfan syndrome also raise the risk.
Traumatic pneumothorax follows a chest injury such as a car crash, a broken rib, a stab wound or a heavy knock in contact sport, or a medical procedure such as a lung biopsy.
What are the symptoms of a pneumothorax?
Symptoms usually start suddenly, often at rest. The most common are:
- sharp, stabbing pain on one side of the chest, usually worse when you breathe in
- shortness of breath, which can be mild or severe
- a dry cough
- a fast heartbeat
How unwell you feel is not a reliable guide to size: a fit young person can have a large air leak with mild symptoms, while someone with COPD can be very breathless from a small one.
When should I call Triple Zero (000) or see a doctor?
A tension pneumothorax develops when air keeps entering the pleural space but cannot get out. Pressure builds, squashing the lung, pushing the heart across and blocking blood flow back to it. It can be fatal without urgent treatment.
Call Triple Zero (000) for an ambulance if you or someone with you has:
- sudden severe chest pain with difficulty breathing
- breathing that is getting worse quickly
- blue or grey lips, fingertips or face
- confusion, drowsiness, fainting, or a racing pulse with cold, sweaty skin
- chest pain or breathlessness after a chest injury
For milder symptoms, such as new one-sided chest pain with slight breathlessness in someone who is otherwise well, see a doctor the same day or go to an emergency department: only a chest X-ray can tell a pneumothorax from heart problems, a blood clot in the lung (pulmonary embolism) or a muscle strain. Do not drive yourself there.
How is a pneumothorax diagnosed?
Your doctor will ask about the pain, any chest injury, smoking or vaping and lung conditions, and listen to your chest; breath sounds are often quieter on the affected side.
The main test is a chest X-ray, which shows the edge of the collapsed lung and lets the doctor estimate the size. A CT scan may be arranged if the X-ray is unclear, if the pneumothorax keeps coming back, or to look for blebs and underlying lung disease before surgery. If a tension pneumothorax is suspected, treatment starts immediately, before any imaging.
How is a pneumothorax treated?
Treatment depends on the size of the pneumothorax, how much it is affecting your breathing, and whether you have another lung disease. Current guidelines favour the least invasive option that is safe for you.
Watching and waiting (conservative management). If you have a primary spontaneous pneumothorax with only mild symptoms, you may not need a procedure at all, even if it is fairly large. A large trial run mainly in Australian and New Zealand hospitals found that people treated this way healed just as well by eight weeks as those given a chest drain, with fewer complications. You will be checked with repeat X-rays and told exactly when to come back.
Needle aspiration. Under local anaesthetic, a thin tube is passed between the ribs and the air is drawn out with a syringe. This is often the first step for a larger primary pneumothorax with symptoms, and many people go home a few hours later after a check X-ray.
Chest drain. If aspiration does not work, or the pneumothorax is secondary or traumatic, a small flexible tube is placed between the ribs and connected to a one-way valve or underwater seal that lets air out but not back in. It usually stays in for a few days until the lung has re-expanded and the leak has sealed. Selected patients can go home with a small portable valve and be reviewed every day or two.
Surgery. Keyhole surgery (video-assisted thoracoscopic surgery, or VATS) is done under general anaesthetic through two or three small cuts. The surgeon removes the blebs and makes the lung stick to the chest wall (pleurodesis) so it cannot collapse again. It is usually advised after a second pneumothorax on the same side, a first on the other side, an air leak that will not seal, or a first episode in someone with a high-risk job such as flying or diving. If surgery is not suitable, talc powder can be put through the chest drain to achieve the same effect (chemical pleurodesis). Sleep and Lung Care’s thoracic surgery service assesses patients for keyhole surgery.
How long does a collapsed lung take to heal?
The body reabsorbs trapped air slowly, roughly 1 to 2 per cent a day. A small pneumothorax left to heal on its own usually clears within one to two weeks, while a complete collapse can take up to about six weeks. Most people are back at desk work within a week or two; heavy lifting, strenuous exercise and contact sport usually wait until the follow-up X-ray shows the lung has fully expanded. Two travel rules are important:
- Flying: do not fly until at least seven days after a chest X-ray confirms the pneumothorax has completely gone, because any remaining pocket of air expands at cabin altitude.
- Scuba diving: after a spontaneous pneumothorax, diving is generally advised against for life, even after surgery, because a recurrence under water can be fatal; anyone who wants to dive again needs assessment by a diving medicine doctor.
If you smoke or vape, stopping is the single most useful thing you can do to prevent another episode; your GP and Quitline (13 7848) can help.
Will a collapsed lung happen again?
It can. Around one in three people who have a primary spontaneous pneumothorax have another on the same side, most often within the first couple of years, and the risk climbs after a second episode. Recurrence is also common after a secondary spontaneous pneumothorax, and continuing to smoke raises the risk further. Surgery with pleurodesis cuts the chance to a few per cent, which is why it is recommended once a pneumothorax has come back.
When to see a respiratory physician
Everyone who has had a pneumothorax should be reviewed by a respiratory physician (a specialist lung doctor), ideally within two to four weeks, to confirm on a repeat chest X-ray that the lung has fully re-expanded, to look for underlying lung disease with lung function tests and, where needed, a CT scan, and to talk through recurrence, surgery, flying, diving, work and sport. Ask your GP for a referral to Sleep and Lung Care’s respiratory physicians. New patients are seen in person at Epping, Brunswick, Doncaster East, Braybrook or Kilmore so that examination and testing happen at the same visit; lung function tests are bulk billed with a GP referral, and follow-up can be by video consultation where appropriate.
Frequently asked questions
Can a small pneumothorax heal on its own?
Yes. A small pneumothorax in an otherwise healthy person often reabsorbs by itself over one to two weeks. Your doctor may monitor you with repeat chest X-rays rather than draining the air, provided you are not very breathless and can get back to hospital quickly if symptoms worsen.
How serious is a collapsed lung?
It ranges from a minor problem to a life-threatening emergency. A small pneumothorax in a young, healthy person usually heals fully without lasting damage, but a large one, one in someone with lung disease, or a tension pneumothorax can become dangerous quickly. Sudden chest pain with breathlessness always needs a chest X-ray.
How long after a collapsed lung can I fly?
The British Thoracic Society’s BTS air-travel guidance advises waiting at least seven days after a chest X-ray confirms the pneumothorax has completely resolved, because trapped air expands at altitude. If you have had a chest drain or surgery, or have an underlying lung condition, check with your respiratory physician before booking, especially long-haul flights.
Is a collapsed lung caused by smoking or vaping?
Smoking does not cause every pneumothorax, but it is the strongest risk factor you can change: smokers are many times more likely than non-smokers to have one, and continuing to smoke raises the chance of it happening again. Vaping has been linked to pneumothorax in a growing number of case reports, so stopping both is strongly advised.
References
- healthdirect — Pneumothorax — 2025
- NSW Agency for Clinical Innovation, Emergency Care Institute — Spontaneous pneumothorax — 2026
- British Thoracic Society — BTS Guideline for Pleural Disease (Roberts ME et al., Thorax) — 2023
- British Thoracic Society — Clinical Statement on air travel for passengers with respiratory disease — 2022
- Cheng HS et al., Journal of Thoracic Disease — Management of spontaneous pneumothorax: a mini-review on its latest evidence — 2024
- Mellor C, Davidson R, Pippard B, Journal of Thoracic Disease — Vaping-related lung disease: a narrative review — 2026
